Location :
Orlando, FL, USA
 +1 (407) 714-1616
 info@biz4group.com

















Imagine a digital system that doesn’t wait for instructions but instead, understands your business goals, learns from real-time feedback, and takes independent actions to get the job done.
Read More

 AI Summary Powered by Biz4AI
Ask any hospital CTO what keeps them up at night and AI comes up in the first five minutes. Not because they doubt it works. Because they have watched too many vendors promise a smart assistant and deliver a chatbot with a medical dictionary bolted on.
Here's a number that puts things in perspective. As of early 2026, 75% of U.S. health systems run at least one AI application in production, up from 59% just a year before. The AI agent market specifically has caught up just as fast, reaching $10.9 in 2026, as per Grand View Research. That is not hype. That is a market where the organizations moving now, with the right foundation, end up ahead of the ones who wait and rush later.
So, if you are asking whether healthcare AI agent development is worth exploring, the market already answered that. The real question left on the table is different. How do you build one that actually holds up once it is touching patient data, talking to Epic or Cerner, and getting reviewed line by line by a compliance officer who has seen software fail before?
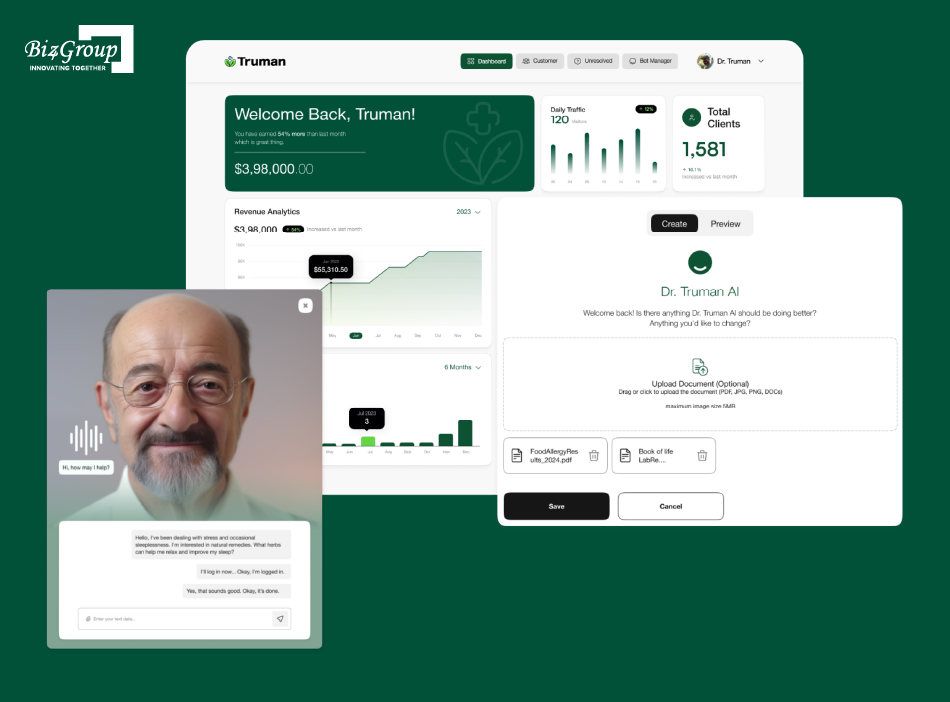
We are Biz4Group, and healthcare is one of the industries we know from the inside, not just from documentation. When we built an AI-powered health avatar for a wellness client, it drove a 40% increase in user engagement and a 30% lift in product recommendations accepted, inside a system that had to stay compliant from day one. We have also had the harder conversations, the ones where a client's own legacy system was the real bottleneck, not the AI. That experience is part of a much larger shift happening right now, as agentic AI in healthcare moves from pilot projects into everyday clinical and administrative workflows.
Healthcare AI agent development is a different discipline than building AI agents for retail, finance, or customer support. The stakes are higher, the integrations are messier, and the regulations do not forgive shortcuts. What happens when a medical AI agent gets a drug interaction wrong, or a hospital AI agent exposes patient data through a sloppy API call? The cost of getting it wrong here is not a bad review. It is a HIPAA violation, a lawsuit, or worse, a missed diagnosis.
This guide walks through it the way we walk our own clients through it before anything gets built: what these agents actually are, what they cost in 2026, and how to choose a partner who gets it right the first time.
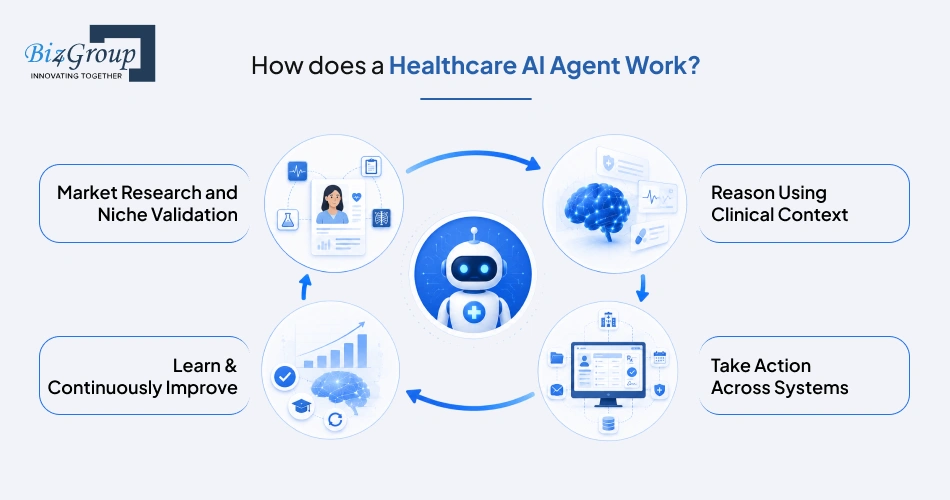
A healthcare AI agent is software that perceives a task, reasons through it using patient or system context, takes action inside connected healthcare systems, and improves its own decisions from the outcome, all without a human directing every step. That's the definition we work from at Biz4Group, refined over two decades of building AI systems for hospitals, clinics, and health tech firms, not something pulled from a glossary. It matters because most of what gets marketed as an "AI agent" in healthcare right now is a scripted chatbot wearing a new label.
Here's the line that actually separates the two. A script follows fixed rules and breaks the moment reality doesn't match them. An agent makes a judgment call inside boundaries you define and keeps working even when the situation shifts. That distinction is the whole reason healthcare AI agent development exists as its own discipline instead of falling under regular automation.
Every real agent runs on the same four-step loop, whether you build an AI agent for healthcare, retail, or finance. What changes in healthcare is how tightly each step has to be governed, and we've seen firsthand where teams cut corners on this.
The agent pulls in the input it needs to act, a patient message, a lab result, an EHR update, and a scheduling request. This step has to respect access controls by design, not as an afterthought. When we built a conversational support system for at-risk veterans dealing with mental health concerns, the agent could only perceive the specific context it was cleared for, nothing from a user's broader medical record beyond what that conversation required. That kind of scoped access is what separates a compliant medical AI agent from a liability.
A language model, usually paired with a retrieval layer pulling from your clinical or policy data, works out what the input actually means and what should happen next. Accuracy here lives or dies on how well that retrieval layer is grounded in real, current data, not on how capable the underlying model is on paper.
The agent calls a tool, an API, a database query, a message to a patient portal, and executes the decision. Every action needs to be logged and traceable. An action nobody can trace back later isn't a feature gap, it's a compliance gap waiting to surface during an audit.
Outcomes feed back into the system so the next decision improves on the last. This is trickier in healthcare than anywhere else, because that learning loop has to happen without training on raw patient data in ways that violate HIPAA. We ran into exactly this constraint building a cognitive support tool that used machine learning to track dementia progression over time. The system had to keep improving without ever retaining identifiable patient data outside its permitted scope, which shaped the entire memory architecture from day one.
One structural decision worth knowing before you scope anything: should this be one agent doing everything, or several agents each handling a narrow job? A single agent trying to triage patients, file claims, and manage scheduling ends up mediocre at all three. Most hospital AI agent deployments we're seeing succeed in 2026 use multiple narrow agents instead, a triage agent, a billing agent, a scheduling agent, that hand off context to each other when a task crosses lanes. That's a call you make at the architecture stage, not something you patch in later, and it shapes everything downstream, from cost to how fast compliance review moves.
Most teams find out too late that the real blocker was never the AI. Let's figure out where you actually stand before you spend a dollar on development
Get a Free Readiness Check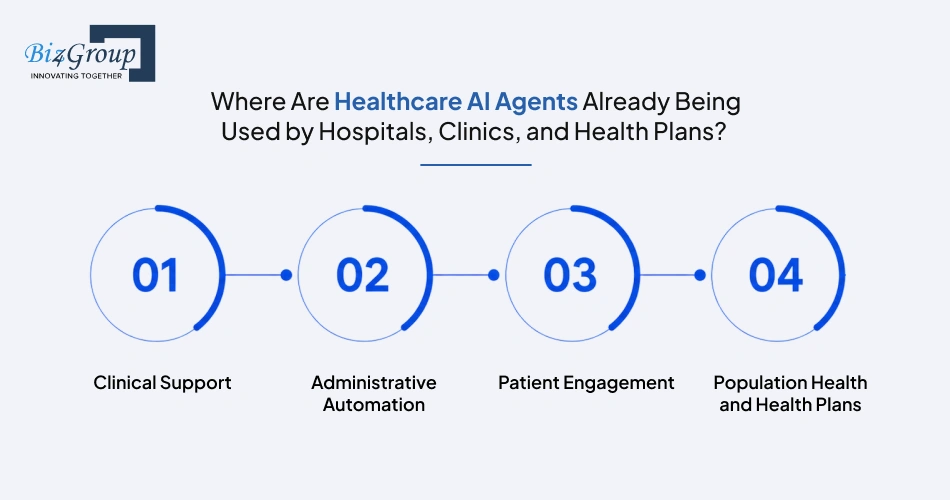
This isn't a future-tense conversation anymore. Hospital AI agents are running in production right now, inside real health systems, handling real patient and administrative work. Here's where healthcare AI agents are actually making a difference, broken down by function.
Clinical support agents sit alongside physicians during patient visits, listening to the conversation and drafting structured notes in real time. They pull relevant history from the EHR before the physician even asks, and flag anything in a patient's record that might affect the current visit. An AI clinical support agent built well is the use case with the fastest documented return, because it removes hours of after-hours charting that most physicians are doing unpaid. The same underlying logic extends into triage, where an AI medical agent for patient interaction and triage can flag urgency before a nurse even opens the chart.
Example
At Mass General Brigham, an ambient scribe deployment saved physicians roughly four hours a week on documentation, time that went straight back into patient care instead of typing notes after the last appointment of the day. That's not a projection. That's a measured result from a live deployment.
Administrative agents take on the paperwork that eats up billing and prior authorization teams, pulling clinical documentation, checking payer criteria, submitting requests, and tracking approvals without a human touching every step. Health systems investing in healthcare AI agent integration services for this layer tend to see the fastest dollar-for-dollar return of any use case, because the process being automated is repetitive, rule-heavy, and painfully slow when done by hand. This is also where custom AI agents for healthcare administrative teams tend to outperform off-the-shelf tools, since payer rules and internal workflows rarely match a generic template.
Example
A mid-sized health system running a 200-plus bed hospital and more than 50 outpatient clinics deployed a multi-agent prior authorization system that cut turnaround from 14 days to under 3 hours, automating 85% of a workload that previously required a team of 12 full-time coordinators processing over 2,800 requests a month.
Patient-facing agents handle scheduling, appointment reminders, medication follow-ups, and routine questions, all without a patient sitting on hold. Done well, this is where a conversational AI agent stops feeling like a chatbot and starts feeling like a front desk that never closes. This is one of the most common entry points for healthcare AI agent for hospitals and clinics looking for a first project, since the upside is measurable fast: fewer no-shows, recovered revenue, and less time lost to delayed care.
Example
El Rio Health, a federally qualified health center in Arizona, reduced no-show rates by 32% and increased monthly revenue by $100,000 after deploying AI-powered appointment reminders across its patient base.
At the health plan level, agents work across claims, eligibility, and outreach instead of a single patient interaction. This is where healthcare AI agents cost for health plans becomes a real budgeting question, since payer-side agents typically operate at higher volume and higher integration complexity than a single clinic's scheduling bot. This tier is usually where enterprise healthcare AI agent development enters the conversation, because a payer's systems, member volume, and compliance surface area are simply bigger than a single provider's. Done right, this is also where an AI multi-agent preventive care ecosystem starts to pay off, catching risk patterns across a member population before they become expensive claims.
Example
One health system's claims appeals process, previously taking 15 to 16 days with manual nurse review, dropped to 1 to 2 days after an AI agent took over reading denial letters, assembling corrected documentation, and routing appeals for nurse sign-off, according to reporting from HealthTech Magazine.
Four different use cases, four different outcomes, and the same underlying pattern each time. The agent didn't replace the team. It removed the part of the job that was slow, repetitive, and never needed a medical degree to begin with.
Compliance in healthcare AI agent development isn't one rule you check off. It's a stack of regulations, each covering a different failure point, and missing any one of them can shut a deployment down after it's already live. Here's what actually applies, laid out the way a compliance officer would actually ask about it.
Six frameworks apply in most real deployments: HIPAA, HITECH, FDA guidance on clinical decision support, 21 CFR Part 11 for electronic records, GDPR if you touch any EU patient data, and the EU AI Act for organizations operating internationally. None of them carve out an exception because a model made the decision instead of a person. If the action involves patient data or a clinical outcome, the same rules apply whether a nurse did it or an agent did.
Under 45 CFR §164.312(a)(1), technical access controls have to limit ePHI access to authorized persons or software programs, and that language covers an agent directly. The same minimum necessary standard that governs a nurse's EHR login governs what your agent is allowed to query. An agent with broader access than it needs isn't a convenience, it's an open compliance finding waiting for an audit.
Any AI vendor processing PHI on your behalf becomes a business associate under HIPAA, full stop, regardless of what other certifications they hold. That agreement has to cover every service in the stack, including the model provider and any subcontractor touching your data, not just the headline product. If a vendor can't produce a BAA that names the actual infrastructure your data runs on, that's a disqualifying answer, not a detail to work around.
At minimum: encryption at rest and in transit, role-based access control, session-level authentication, and audit logs that record every action the agent took and why. Under §164.312(b), the absence of audit records is itself a violation, separate from whatever incident it failed to catch. This is also where working with a proven HIPAA-compliant AI healthcare software development company matters, since these controls have to be built into the architecture, not patched on after a security review flags a gap.
If your agent influences a clinical decision rather than just automating admin work, it may fall under FDA clinical decision support guidance or even Software as a Medical Device rules, depending on how much autonomy it has. This is the piece most HIPAA compliant AI agent development conversations skip entirely, and it's exactly why scoping a clinical-facing agent needs a compliance conversation before a single line of code gets written, not after.
Get this part wrong and every other part of your build, the tech stack, the cost estimate, the timeline, gets rebuilt around a compliance fix later. Get it right from the start and it barely slows you down.
A useful healthcare AI agent needs seven core features that solve real day-to-day problems for patients, providers, and administrative staff. These are the things a clinic director or hospital CTO actually points to when deciding whether an agent earns its place in daily operations. Here's what each one does.
This lets patients book, move, or cancel appointments through text, voice, or chat, any time of day, without waiting on hold or working within office hours. When a provider cancels, the agent can also fill that slot automatically instead of leaving it empty. This single feature of AI appointment scheduling is usually the fastest path to measurable ROI, since a filled slot is direct revenue and a missed one is a real financial loss.
This handles the questions a patient usually answers on a clipboard before ever seeing a provider, symptoms, history, current medications, and flags anything urgent before the visit even starts. It saves front-desk time and gives the clinician a head start instead of a blank slate. Done well, it turns the first five minutes of a visit into actual care instead of paperwork.
This listens to a patient visit and drafts a structured clinical note in real time, pulling the right terminology and formatting without the physician typing a word. It's the feature behind the four hours a week in saved documentation time we covered earlier in this guide. For most physicians, this alone is the difference between finishing charting at 5pm or finishing it at 9pm.
This reaches out to patients based on their actual prescription schedule and care plan, not a generic reminder blast sent to everyone on the same day. It catches missed refills, upcoming follow-ups, and gaps in a care plan before they turn into a bigger problem. This is one of the simpler features to build, but it consistently shows up as one of the highest-impact ones for patient adherence.
This checks a patient's coverage and handles the prior authorization paperwork before a procedure, instead of a staff member spending hours on payer phone calls. It's the feature tied directly to the 14-day-to-3-hour turnaround example we covered in the use cases section. For any clinic or hospital drowning in administrative overhead, this is usually the first feature worth prioritizing.
This flags anything that needs immediate human attention, a concerning vitals trend, a high-risk lab result, a patient message that reads as urgent, and routes it to the right person instead of sitting in a queue. It's what keeps an agent from quietly missing something serious while handling routine tasks. This feature is non-negotiable for any AI clinical support agent operating anywhere near patient safety decisions.
This lets the agent handle conversations in a patient's preferred language instead of defaulting to English and hoping for the best. For any hospital or clinic serving a diverse patient population, this isn't a nice-to-have, it's often a real access-to-care issue. It also tends to reduce reliance on scheduling human interpreters for routine, low-complexity interactions.
Seven features, each one solving a specific problem someone on your staff or in your patient population deals with every day. This is also the list worth testing first in any early healthcare AI agent development rollout, since these are the features that prove value fast enough to justify building further.
Advanced features are what separate a genuinely capable agent from one that handles the basics and nothing more. These aren't required to launch, but they're what makes an agent handle complexity, scale across departments, and hold up in real clinical decision-making instead of just administrative tasks. Here's the full set worth evaluating for intelligent healthcare agent development.
|
Advanced Feature |
What It Does |
Why It Matters in Healthcare |
|---|---|---|
|
Pulls live, current medical data into the agent's response instead of relying only on what the model was trained on |
Keeps clinical answers grounded in your actual protocols and current guidelines, not outdated training data |
|
|
Coordinates several specialized agents, triage, billing, scheduling, working in parallel and handing off context to each other |
Core to real AI agent orchestration for healthcare, since one agent trying to do everything ends up doing all of it poorly |
|
|
Federated Learning |
Trains a model across multiple hospitals or systems without any raw patient data ever leaving its source |
Allows institutions to improve accuracy together without violating data-sharing restrictions |
|
Long-Term Memory and Vector Search |
Stores and recalls patient history and past interactions across sessions using vector databases |
Makes the agent feel consistent to a returning patient instead of starting from zero every visit |
|
Multi-Modal Input |
Accepts text, voice, and images, letting a patient upload an X-ray or describe symptoms out loud |
Widens who can actually use the agent, including patients who struggle with typing or forms |
|
Flags patients trending toward a health event before symptoms become obvious |
Turns the agent from reactive to preventive, catching problems earlier in the care timeline |
|
|
Reads emotional signals in a patient's message or voice, not just the literal words |
Critical for mental health, teleconsultation, and any agent handling a distressed or anxious patient |
|
|
Voice-First Interface |
Lets clinicians and patients interact hands-free through natural speech instead of typing or clicking |
Fits real clinical settings where a physician's hands are occupied or a patient can't easily type |
|
Explainability Layer |
Shows the reasoning behind an agent's suggestion instead of returning a black-box answer |
Builds physician trust, since clinicians need to understand why before acting on an AI recommendation |
|
Agent-to-Agent Handoff |
Passes context between agents mid-task so a patient never has to repeat themselves across departments |
Makes a healthcare AI agent platform development effort feel like one system instead of five disconnected bots |
None of these are required on day one. What we usually recommend to clients building an enterprise AI agent for a larger health system is to launch with core features first, prove the value, then layer in the advanced ones based on where the real bottleneck shows up. Multi-agent orchestration and RAG tend to earn their place fastest, since they directly affect accuracy and coordination. Federated learning and predictive risk scoring usually come later, once there's enough data and enough trust in the system to justify the added complexity.
RAG, multi-agent orchestration, predictive risk scoring, not every feature belongs in version one. Let's map out which ones are worth your budget and which can wait
Talk Through Your Feature Roadmap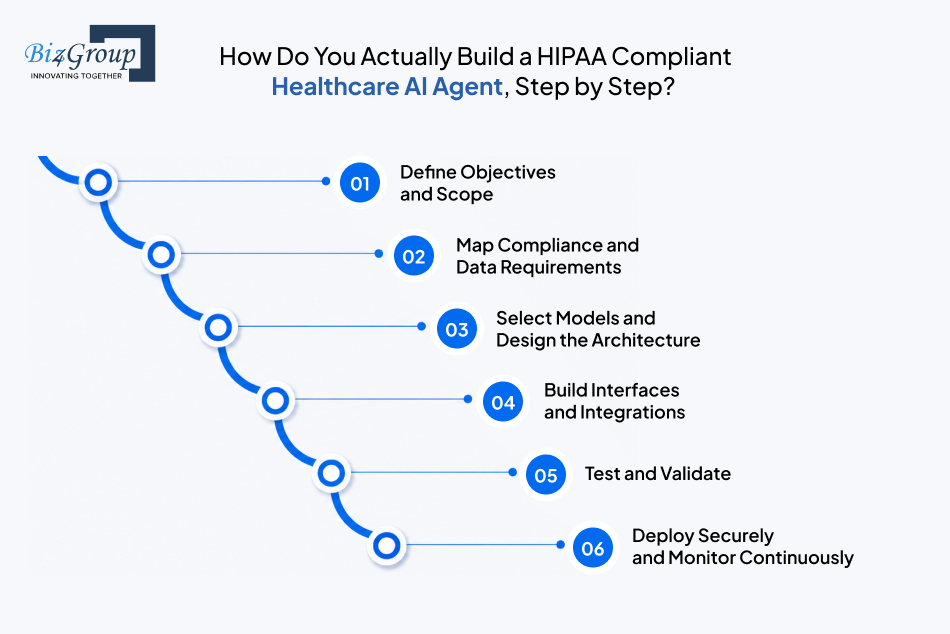
Building a HIPAA compliant healthcare AI agent follows six steps, and compliance has to be designed into each one, not bolted on at the end. Skipping ahead to development before this sequence is complete is exactly how teams end up rebuilding half the system after a security review. Here's how it actually works.
Before any code gets written, you need clarity on exactly what the agent will do, who it serves, and how success gets measured. Most teams starting healthcare AI agent development for the first time do better launching a focused build rather than trying to solve five problems at once. This is also usually where an MVP development approach earns its place, proving value on one workflow before expanding.
This is where you define exactly what data the agent can access, what it can do with it, and which regulations apply to each action it takes. Getting this wrong doesn't just create legal risk, it forces expensive rework later once the architecture is already built around the wrong assumptions. In practice, this step and step one usually happen in the same room at the same time, since what an agent is allowed to do and what data it's allowed to touch tend to define each other as the conversation unfolds.
This is where you choose your foundation model, decide on single-agent versus multi-agent structure, and plan how retrieval and memory will work. The model choice matters less than most teams assume, the architecture around it is usually what determines whether the agent actually performs. This step also has to confirm the model runs under a proper BAA before a single test prompt touches real data.
This is where the agent gets connected to your EHR, billing systems, and patient-facing portals, and where the actual user experience gets designed. Integration work is usually the most underestimated part of the whole build, since every hospital's systems are wired slightly differently. A strong UI/UX design process matters just as much here as the backend work, since a confusing interface undermines trust in an otherwise solid agent.
This is where the agent gets stress-tested against real and synthetic clinical scenarios before it ever touches a live patient. Hallucination testing matters more here than in almost any other industry, since a confident wrong answer in healthcare has real consequences. This step should never be compressed to save time, it's the last checkpoint before deployment.
This is where the agent goes live inside a HIPAA compliant environment, with monitoring in place to catch drift, errors, or unexpected behavior before they become real problems. Healthcare AI agent deployment isn't a one-time event, it's the start of an ongoing process of watching how the agent performs against real patients and real data. Most teams underestimate how much this step costs, both in tooling and in the people needed to actually watch the dashboards.
Six steps, and the order matters as much as the steps themselves. Skip step two to move faster on step four, and you'll be back at step two anyway, just later and more expensively.
HIPAA compliant AI agent development needs seven layers: frontend, backend, LLM and orchestration, EHR integration, memory and search, compliance tooling, and cloud infrastructure. Miss the compliance or EHR layer and nothing else in the stack matters.
|
Layer |
Technology Options |
Purpose |
|---|---|---|
|
Frontend |
React JS, Next JS |
Powers patient and staff dashboards. Most healthcare AI agent development teams choose Next JS development or React JS development for speed and scalability |
|
Backend |
Node JS, Python |
Runs orchestration logic and API calls. Node JS development handles real-time workflows, Python development handles AI and ML logic |
|
LLM and Agent Orchestration |
GPT-4, Claude, Med-PaLM, LangChain, LangGraph, CrewAI |
Drives reasoning and multi-agent coordination for healthcare AI agents |
|
EHR and FHIR Integration |
FHIR APIs, HL7, Epic and Cerner connectors |
Lets the agent read and write patient data without direct database access |
|
Memory and Vector Search |
Pinecone, Weaviate, Redis |
Stores history and enables fast retrieval for context-aware medical AI agents |
|
Compliance and Security Tooling |
Encryption, audit logging, role-based access control |
Enforces HIPAA, HL7, and BAA-covered data handling at every layer |
|
Cloud and Deployment |
AWS Bedrock, Azure OpenAI, Google Vertex |
Provides BAA-eligible hosting for HIPAA compliant AI agent development |
Two rules matter more than the rest of the stack combined. FHIR-based integration over direct database access, always, since it enforces query-level boundaries instead of open schema access. And only BAA-covered hosting, Bedrock, Azure OpenAI, or Vertex, touches real patient data. Consumer model endpoints are disqualified the moment PHI is involved, no exceptions.
Getting all seven layers right on the first attempt is rare without healthcare-specific experience, which is why most organizations bring in an established AI development company instead of assembling this stack from scratch.
Healthcare AI agent development costs between $20,000 and $200,000, depending on complexity, integration depth, and compliance requirements. That range isn't a shrug, it reflects a real difference between a basic scheduling agent for one clinic and a multi-agent system running across a hospital network. The number that matters is the one tied to your actual use case, not the headline range. For a deeper breakdown across agent types industry-wide, our AI agent development cost guide covers the non-healthcare comparisons too.
|
Feature or Agent Type |
What It Covers |
Estimated Cost |
|---|---|---|
|
Basic scheduling and intake agent |
Appointment booking, FAQs, rule-based logic |
$20,000 – $35,000 |
|
Mid-tier LLM conversational agent |
Triage support, EHR queries, patient communication |
$40,000 – $75,000 |
|
Advanced multi-agent system |
Diagnosis support, billing and claims automation |
$85,000 – $150,000 |
|
RAG integration |
Live medical data retrieval grounded in current guidelines |
+$20,000 – $45,000 |
|
Multi-agent orchestration layer |
Coordinates specialized agents across departments |
+$15,000 – $30,000 |
|
EHR and FHIR integration |
Epic, Cerner, or legacy EHR connectivity |
+$15,000 – $35,000 |
|
Compliance and security layer |
Encryption, audit logging, BAA-covered infrastructure |
+$15,000 – $30,000 |
|
Multi-modal input |
Voice interface, image and X-ray upload |
+$25,000 – $50,000 |
|
Enterprise-grade, multi-department deployment |
Health plan or hospital network scale rollout |
$150,000 – $200,000 |
|
Approach |
What It Means |
Best For |
|---|---|---|
|
Build custom |
Fully tailored architecture, compliance built to your exact workflows |
Hospitals and health plans with unique, high-volume workflows |
|
Buy off the shelf |
Faster launch, lower upfront cost, limited customization |
Small clinics needing quick automation on standard tasks |
|
Hybrid |
Vendor infrastructure paired with a custom compliance and integration layer |
Mid-size providers scaling past a single clinic |
The number you land on depends entirely on which row of that table matches where your organization actually is right now, not where a vendor wants to sell you.
$20,000 and $200,000 are both real numbers, and so is everything in between. Get a straight estimate based on what you're actually building, not a guess
Get Your Real Cost Estimate
Every healthcare AI agent development project runs into some combination of these seven problems. Integration complexity, compliance risk, trust resistance, and cost overruns being the most common.
|
Challenge |
Why It Happens |
How to Solve It |
|---|---|---|
|
Legacy EHR and system integration complexity |
Hospital systems like Epic and Cerner were built decades apart, on different standards, with inconsistent API maturity |
Use FHIR-based integration from day one instead of direct database access, and budget real time for this layer |
|
Data privacy and compliance risk |
Teams treat compliance as a final review step instead of a design requirement |
Map compliance requirements before architecture decisions, and work with a HIPAA-compliant AI healthcare software development company that builds controls in from the start |
|
Clinician and patient trust or adoption resistance |
Staff have seen tools promise efficiency and deliver more clicks, so skepticism is earned, not irrational |
Involve clinicians in testing before launch, and keep human escalation visible so the agent reads as support, not replacement |
|
Model accuracy and hallucination risk |
LLMs generate confident answers even when ungrounded, which is dangerous in a clinical context |
Ground every response in retrieval from your actual clinical data, and run hallucination testing against real scenarios before go-live |
|
Cost overruns and scope creep |
Teams add advanced features mid-build instead of proving core value first |
Launch an MVP on one workflow, validate it, then expand feature by feature with clear cost checkpoints |
|
Scaling across departments without disrupting workflows |
A design built for one clinic breaks when a hospital network rolls it out everywhere at once |
Architect for AI agent orchestration for healthcare from the start, using multiple narrow agents instead of one system stretched thin |
|
Change management and staff training |
Even a well-built agent fails if staff don't know how to work alongside it |
Build a training and rollout plan alongside the technical one, not after deployment |
The projects we've seen go over budget almost always skipped the same step, compliance mapping got pushed past the architecture decision instead of driving it. By the time that gap surfaces, the fix touches code that's already been written twice. Planning around this table before development starts is what keeps a healthcare AI agent implementation on schedule instead of becoming a mid-project rebuild.
The right healthcare AI agent development company has three things in place before you sign anything: hands-on compliance experience, a track record of real EHR or scheduling integrations, and named projects you can actually verify. Anyone can claim expertise on a homepage. What matters is whether they can point to specific work.
Over 20 years and more than 1,000 completed projects, healthcare has stayed a consistent part of that work, not a category added recently to chase a trend. One project maps directly onto what this guide has covered.
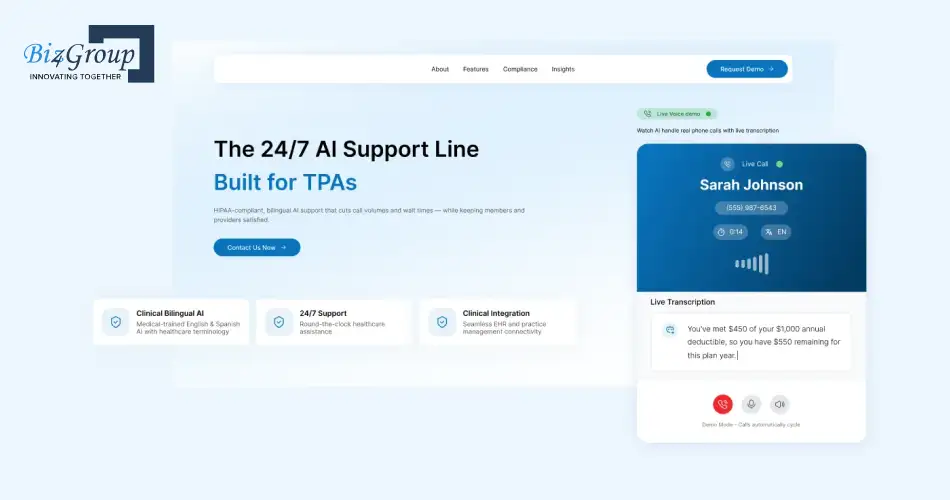
We built a HIPAA compliant AI-driven IVR and support platform for third party administrators in healthcare, replacing outdated phone support that relied almost entirely on live agents for routine calls. The system automates eligibility checks, claim status inquiries, and benefits guidance through natural voice interaction, supports live English and Spanish translation, and escalates complex cases to a human when the conversation calls for it, all while keeping PHI secure throughout. It's the same administrative automation category we walked through earlier in this guide, running on real call volume for a real TPA rather than sitting in a demo environment.
That's the kind of track record worth checking before you commit to any AI agent development company. If you'd rather compare options side by side first, top AI agent development companies for healthcare industry in USA is a useful place to start.
If you're ready to talk specifics, you can hire AI developers who already understand healthcare compliance, instead of learning it on your project.
You've read the whole guide. You know what good looks like now. Let's put it in front of your patients
Book a Free ConsultationEvery question in this guide comes down to the same decision point. Not whether healthcare AI agent development works, the numbers at the start of this piece already answered that. The real decision is whether you build a medical AI agent on a foundation that holds up under a compliance review, or one that looks fine in a demo and falls apart the first time it touches real patient data.
The organizations getting this right aren't the ones moving fastest. They're the ones who mapped compliance before writing a line of code, chose an architecture that matches their actual scale, and picked a healthcare AI agent development company who's shipped this kind of work before, not one learning HIPAA on their timeline. Biz4Group shows up on this list of top agentic AI development companies for healthcare industry in USA, alongside others building in this space, if you want to compare before making that call.
We run a dedicated healthcare AI consulting practice specifically for organizations that are still early in this process, before the architecture is locked, before the vendor is picked, while the use case is still being scoped. That's a different conversation than a sales call, and it's usually the one that saves the most money down the line, since the expensive mistakes in healthcare AI agent development almost always trace back to a decision made in week one, not week ten.
If you're weighing a build right now, start with the smallest version that proves real value, one workflow, one department, and one clear outcome. Get that right, and everything else in this guide, the advanced features, the multi-agent orchestration, the enterprise healthcare AI agent development rollout, becomes a lot easier to justify and a lot cheaper to scale.
Your next patient interaction could be handled by an AI agent for healthcare providers that actually knows what it's doing. Let's build that one together.
Healthcare AI agent development is the process of building software that can understand a task, make a decision using patient or clinical context, take action inside your healthcare systems, and improve from the outcome, all without a human directing every step. It covers everything from scoping and compliance mapping to model selection, EHR integration, and deployment.
Healthcare AI agent development typically costs between $20,000 and $200,000, depending on complexity, integration depth, and compliance requirements. A basic scheduling agent for one clinic sits at the lower end, while a multi-agent system running across a hospital network with EHR integration and advanced compliance tooling sits at the higher end.
A chatbot follows scripted responses and breaks the moment a conversation goes off its expected path. A healthcare AI agent perceives context, reasons through a decision, takes real action inside connected systems like an EHR or scheduling platform, and learns from the outcome. A chatbot answers questions. An agent completes the actual task.
HIPAA compliant AI agent development requires encryption at rest and in transit, role-based access control, audit logging on every action, and a Business Associate Agreement covering the model provider and every subcontractor touching patient data. The agent's access has to follow the same minimum necessary standard that governs a human user's EHR login, nothing broader.
Integration happens through FHIR based APIs and HL7 standards, which let the agent read and write patient data without direct database access. This approach enforces query level boundaries instead of giving the agent open schema access, and it works across systems like Epic and Cerner without requiring a custom rebuild for each one.
A basic healthcare AI agent for a single workflow, like scheduling or intake, typically takes 2 to 4 weeks from scoping to deployment. A multi-agent system with deep EHR integration and advanced compliance requirements can run 4 to 8 weeks, since testing and compliance validation take real time and shouldn't be compressed to hit a launch date.
No. A well built AI agent for healthcare providers takes over repetitive, high-volume tasks like scheduling, documentation, and prior authorization, freeing staff for work that actually needs a human, direct patient care, complex decisions, and judgment calls. Every serious deployment includes a human escalation path for exactly this reason.

Our website require some cookies to function properly. Read our privacy policy to know more.